Friday, February 25, 2022

Last Night in the OR


Routine scheduled surgery during daylight hours always reminded me of church services on Easter Sunday or Christmas Morning, packed with posers and pretenders making a show of strutting their stuff.  Members of the administrative office sitter bunch taking advantage of a new day to spread their feathers like a peacock on parade. The more routine the procedure, the more garish the display.

 Midnight surgeries were of a far different persuasion and akin to a mid-summer church service during vacation season where only the true faithful showed up. The daytime pretenders were a totally different breed from the passionate middle of the night doers. It took a determined personality to crawl out of a warm bed on a frigid Chicago night. Owing to a phobia of authoritative administrators, a craving for an adrenalin boost or a youthful naiveite (choose whatever works for you), I'd rather crawl in for a midnight trauma than scrub for an 8AM vein stripping.

Dr. Slambow, my favorite trauma surgeon had lots to say about these late-night adventures and with his jowls dangling below his mask like a giant croissant he would often bellow. "Everyone here believes in life...so let's get this done before the daytime herd heads through the door." Sometimes he would expound at length as to why the only valid surgical intervention was for serious traumatic injury. "Things can only get better from here, but so many elective procedures invent new surgical complications. When was the last time a radical mastectomy or Whipple really cured anyone?" I could see his point. Thank heaven contemporary surgery with its repair and replace mentality has taken place of the old -ectomy for all free for all's. 

Middle of night surgeries often began with a call to the honeymoon suite which was actually a repurposed vintage operating room at the end of the hall in the oldest part of the hospital. There were 2 sets of bunk beds and a wall phone midway off the floor so it could be answered by upper or lower occupants of the bunk beds. The room's light switch was permanently taped in the off position with autoclave tape, so entrants did not arouse those at rest. Call rooms like this were gender neutral and the only prerequisite for use was being bone tired.

Shenanigans were a great way to pass the time and deal with late night tensions while awaiting that phone call to hop to it. I always tried to set a positive tone for our late-night ministrations and frequently started my dialog with the prep and  a lengthy description how I just loved the radiant pinkish glow of Zephirin scrub solution.

 Janess was a frequent partner on these late-night traumas and I usually bunked on the top bed while we awaited the call god's page. When the call abruptly awakened us at 2AM, a shocker awaited me. I glanced down to put my battle tested Clinics on, and lo and behold, my toenails were painted that lovely pink shade of Zephirin prep solution. Janess just grinned from the lower bunk and admitted she had been busy with nail polish while I was sound asleep.

Janess and I had a long history beginning with a procedure partner pairing in nursing school where we bloodied each others arms attempting IV starts. Like so much that happened during our on call trauma . rendezvous, Janess's presence was a paradox. She presided over emergency surgeries like an angel watching  a cemetery. She was monumental in a demure sort of manner.

The call gods could be an unpredictable lot, but everyone knew to pay close attention to the lunar calendar posted in the light just outside the door. Most nurses did not even bother to rack out when there was a full moon, action was imminent.  

I never gave a thought to circadian rhythms or the pitfalls of staying hyper alert for late night surgeries when I was young and foolish. Trauma surgery was a mission and I had always sensed that I would be completely lost without it. Looking down at blood spattered shoe covers at the end of a rough trauma, I could never imagine not being a part of this mission. This was timeless. 

Later in life looking down at varicose veins and arthritic knees, I came to realize I could be just as lost as a result of it. The very thing I thought I needed the most was the thing that drew the shroud of futility around my soul. Helping others while ignoring self-wellness never has a happy ending. and thankfully, most whippersnapperns are more aware of self care than the Oldfoolrns of days gone by.


Saturday, February 12, 2022

A High-Flying Patient Returns to Earth

 Usually it's a good sign when you  hear a patient coming through the ER with their shrieks echoing off the green tile walls, but with this one, there was a twist. The disheveled, emaciated gentleman was chanting, "I'm breaking a record. get me back up there." Strange indeed.

As I approached him, a strange combination of olfactory stimuli assaulted my prominent, sensitive beak, a sweet-sour miasma of cigarette smoke and Old Spice cologne to mask the imbedded dirt that made his skin look like a Jackson Pollack work of abstract art. The combination of different colored dirt and a panoply of greenish fungal lesions was a sight to behold.

 I checked the skin turgor on an atrophied bicep and the little mountain of skin generated by the gentle pinch had the staying power of a member of the nurse academic/administrative office sitter complex ensconced in a Lazy Boy recliner. This poor soul was severely dehydrated.

Of course, in pre-EMS days, the Chicago Police were responsible for most patient transfers, and it was prudent to pay heed to the officer's admission commentary for a history of the patient's injury or treatment insights. The jolly young officer presenting us with our latest challenge had an unusual warning that really piqued our curiosity, "You better be able to rehabilitate this one or you're going to have to order a sitting 'em up coffin for him." Sure enough, the unveiling accomplished by an Abra Cadabra top sheet removal revealed some of the most severe lower leg contractures I have ever seen, with his knees flexed at a 45-degree angle so that a conventional flat, horizontal coffin would never accommodate him. This patient was a poster boy for the hazards of immobility.

No, this was not a nursing home patient. It was obvious from the poor soul's wrinkled, weathered, and deeply tanned skin that he had spent considerable time communing with the natural world in the good old outdoors. His well tan, wrinkled extremities had the color of tobacco juice and upon removing his tee shirt emblazoned with the slogan "ANGER MANAGEMENT PISSES ME OFF," a few scraggly chest hairs emerged from a chest that looked like the color of skim milk.

Perhaps a hiker who experienced a mishap on the trail or a construction worker? The patient was strangely nonverbal when queried about his plight, and as the mystery deepened, we decided that treating his dehydration would be a good place to start. His serum osmols were sky high and poor skin turgor cried out for hydration. 

We lacked that clever whippersnappern vernacular back in the day, but the new fangled  term "fluid resuscitation" described what was acutely needed here. Unfortunately, a cursory review of his arms revealed that finding a vein was going to be like looking for a black cat in a coal mine. I corralled the friendly resident to place a central line. He opted to place it in the subclavian vein running just below the clavicle. He punctured the big vein with ease and after verifying a good, nonpulsatile flow began threading the guide wire through the needle. After sliding the catheter in we were in business.

It didn't take long for our efforts to bear fruit and the poor soul began relating his adventurous, but misguided tale. He had been hired by a newly established whiskey distillery on Lincoln Avenue to set a flag pole sitting record as a publicity stunt. This activity, popular in the 1920s and resurrected in the 1960s was exactly as described. Our patient had been confined to a whiskey barrel platform erected on the very tip of a 60 foot flag pole. He was planning to break a 30 day record but was retired after several weeks when his ground crew could not communicate with him and called the Chicago police who delivered him to our ER. 

What goes up, must come down

Before internet advertising, business had to invent a number of  whacky schemes to promote their ventures. Oscar Mayer company had a vehicle resembling a hot dog on 4 wheels aptly called the wienermobile and it was piloted by none other than Little Oscar. Car dealerships used high voltage floodlights to illuminate the night sky and bring in customers. Like the emaciated flag pole sitter some of these promotions ended in a trip to the hospital. Lincoln Mercury had a genuine Cougar on hand at Chicago's Ampitheater auto show and all was hunky dory until the beast attacked his trainer.

It's a good reason that hospitals were not allowed to advertise or I suspect misguided CEOs would have considered a nurse for flag pole sitting duty. They expected us to perform just about any unsavory or unpleasant task imaginable.


'  

Sunday, January 30, 2022

Thursday, January 27, 2022

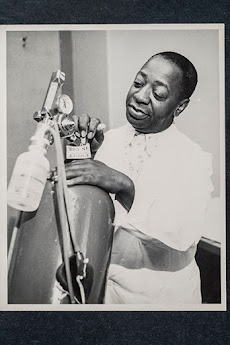
Life Before Piped in Oxygen - Tanks A Lot

Physiology pivots on the oxygen pinnacle

I thought those gigantic "H" cylinders of oxygen, not to be confused with their lesser sized brotherern, would be with us forever in the hospital. Oxygen delivered to wall outlets in patient's rooms seemed like a pipe dream because we had enough problems with our common old ordinary plumbing. There were steam leaks from autoclave pipes that resembled Old Faithful and recurrent problems with clogged drains. Pipes and problems went together like tweedle dee and tweedle dumb. How in the world could this ever work with a gas under high pressure?

I couldn't imagine oxygen pipes being exempt from similar pipe problems and, of course, I was an ace with the skills necessary to course these massive green cylinders around and about hospital wards and halls. Who needs fancy piped in O2?  A weak mind and a strong back were the only prerequisites for being an oxygen delivery boy, and of course the eager nurses and cyanotic patients were always overjoyed to see me with my life sustaining cargo. Just what a fragile adolescent male cast adrift in a sea of estrogen needed for an ego boost. I was really doing something worthwhile! This is why I chose nursing as a career instead of an auto mechanic.

Oxygen tank storage rooms were special places and out of bounds for most of the fairer sex. Green monsters chained to 2X12 wooden planks and weighing in at over 150 pounds required some muscle and lots of practice to safely handle. I used a trusty dolly to transport these bemouths and once they were set in motion inertia took over. Stopping these rolling monsters was akin to putting the brakes on a battleship.

The other tricky part was maintaining the correct incline while tipping the dolly into position. There were dollys with training wheels for the more cautious, but the tiny caster like wheels used on the trainer support system were prone to gyrating like a belly dancer and slowing the entire delivery process. It was no fun pushing these bruisers down a hospital corridor with those tiny wheels doing the watutsi.

Training wheels also impaired the ability to maneuver the tank into position at the patient's bedside. It was possible to fine tune the position of the tanks when it was released from the dolly by carefully rolling the base of the tank which was all fun and games until you rolled an "H" cylinder over your toes. I preferred the dolly sans training wheels.

Alas, all good things must come to an end, and the conversion of cavernous hospital wards to semi-private rooms was a game changer. Wrestling a colossal "H" oxygen cylinder into the cramped confines of puny 2 bed hospital room was akin to stuffing an elephant into a phone booth, these green monsters longed for the circus big top of a spacious ward where there was ample room to roam.

The construction required to section off individual rooms from the big tent arena of a hospital ward provided an opportunity to run pipelines for the bedside delivery of oxygen, and an end to wrestling with the big green monsters.

Endings like this are usually bittersweet. Yes, piped in oxygen was very convenient, but the bedside delivery of something as life sustaining as oxygen afforded the delivery boy an entire cosmos of goodwill. It was heartwarming to witness the relief and gratitude of patients and nurses alike, while I quickly switched out regulator yokes and twisted my oxygen wrench to the on position and noted the swing of the needle on the pressure gauge from near empty to full, good for another few days of life sustaining oxygen. I was transformed from lowly delivery boy to a genuine care giver and that was good enough for me.


Monday, January 3, 2022

Roller Clamps Were Pioneers in IV Fluid Regulation


The past is like a foreign country where things are done differently, before the extravagant complexity of intravenous pumps and controllers, simple little roller clamps ruled the roost when it came to IV regulation. I was totally fascinated by these clever little gizmos and even had a collection of vintage roller clamps that I recently unearthed from my nursing archives basement junk hoard. 

These unsung heroes of the IV therapy universe deserve further study as they are not as simple as they appear. An injection molded cage with wheel guides molded into the sides to accept the axles of the adjustment wheel is the most obvious feature. When the wheel is positioned at the top of the housing an uncompromised flow of IV fluid ensues. The device must apply just the right amount of friction to the plastic tube to remain stationary while leaving the lumen of the IV tube wide open, not an easy task. The device then had to regulate the flow of IV fluid by changing the lumen of the IV tubing as the nurse turned the adjustment wheel.

There was strict dogma delineating the correct position of the clamp on the tubing.  Our rigid, uncompromising diploma school instructors insisted on having the roller clamp positioned about 2 inches below the drip chamber so as to be able to locate it in the dark. Old nurses never, ever flashed on blinding overhead room lights at night. Sleep was revered as a healing agent. Having the clamp just below the drip chamber made it easy to locate at night.

There were 2 methods of establishing a flow control region within the clamp housing and one entailed the wheel traveling along an inclined ramp molded into the bottom wall of the device. The other entailed a clamp with the base parallel to the open wheel access port, not a ramp in sight!  The wheel guides were inclined so the wheel traveled at an angle to the base of the clamp whereas the wheel was much closer to the bottom of the clamp when rolled down. The pressure on the IV tubing was varied by the up and down movement control wheel as it moved along the inclinations in the wheel guides.

Some really fancy roller clamps were dual action in that both a ramp and a variable inclinable control wheel changed the lumen of the IV tube. Some things in nursing made no sense and one of the most common places to find these over engineered, exquisite roller clamps was on clysis sets that were used to give fluids subcutaneously. Drip regulation on clysis sets was not a big deal, so why the fancy roller clamps?  Some mysteries are never solved, especially in nursing, but that's a topic for another day.

 Clysis sets were really old school and not subject to medical supply companies seeking to maximize profit margins by making cheaper roller clamps. Travenol clysis sets with dual action clamps even had metal axle spindles on the control wheels. I'm sure it would have been more cost effective to injection mold the wheel and axle in one piece. No cost was spared in producing these roller clamp gems.( For more foolishness on clysis:  https://oldfoolrn.blogspot.com/2015/07/down-quart-hypodermoclysis-to-rescue.html . )

One of the problems with roller clamps was a phenomenon called control point drift which occurred when the control wheel spontaneously moved to a region of less pressure increasing the lumen of the IV tube resulting in increased flow rate. Definitely not a good thing, especially when titrating vasopressors. The dual action clamps with metal control wheels were rock solid once adjusted. The increased  friction exerted by the metal spindles effectively attenuated control point drift.

Another problem with roller clamps involved the properties of the PVC intravenous tubing itself. After adjustment a phenomenon known as cold flow creep sometimes occurred. The lumen of the IV tube would decrease even though there was no movement of the control wheel. Lengthening the control zone on the clamp helped control this problem. Generally speaking, the longer the roller clamp the more stable the infusion rate. Short, stout roller clamps could be a real bear to regulate, some nurses even resorted to taping the control wheel in place.

The labor investment required by manual IV control was considerable because roller clamps needed frequent adjustment, but who would you like to see standing at your bedside, a concerned nurse or a noise barfing electronic poseur? Roller clamps also limited the number of IVs that could be managed on a ward. On a 30 bed unit the maximum number of  running IVs was abour six. Roller clamps are long gone, but not forgotten.

Wednesday, December 15, 2021

Rethinking Nursing Awards

It's been many moons since I've posted and I'm certain all three of my regular readers miss my foolishness as much as I miss their astute comments. When it comes down to posting on my blog or navel gazing, the later always seems to win out.

 I wonder how anyone can be a regular reader of an intermittent blogger  unless they are like regularly irregular like cardiac arrhythmias,...oops there I go with more of that philosophical navel gazing stuff. Well it's time to grind out some of that patented foolishness that I'm famous for and what better place to start than with that time honored tradition of nursing awards?

I've  noted a recent plethora of nonsensical  nursing awards. Let's see there is the ever popular Daisey award and the Rubber Duckey award (No foolin'). One medical center was even handing out rocks as an award. Strange indeed. Most of the folks handing out nurse awards are hard core members of the dreaded nurse academic/administrative office sitter complex who have mastered a type of feel good jargon with absolutely no clue about what actually transpires during bedside nursing care.  Without further ado let's get into some real world nursing awards from the perspective of the tried and true bedside practitioner.

The first award is the aptly named The Golden Goose award which is given to the most whacky and useless nursing research project. I never could deduce the role of nursing research which should be aligned with biology and physiology, not psychology and sociology. What's wrong with clinical research if our goal is to improve patient care?

Drumroll please...the Golden Goose is awarded to a study with the impressive question; "Does photic stimulation impact hypovigilant states in the hospitalized patient?" If a research question can be easily answered, it's probably not a good one to study, and heck yes, turning on the sonic boom equivalent of lighting in a hospital room wakes patients up. We used to sneak around with great stealth using flashlights so I cannot understand where the notion of turning on the bright overhead lights came from.

I suspect it might have something to do with utilization review nurses and their never-ending quest to give patients the boot out the front door ASAP. Making the hospital environment as inhospitable as possible is a fail safe method to encourage patient egress in an expedicious manner.


My next award is aptly named "The Bermuda Triangle" and Head nurse Annie whose exploits I've detailed in a previous post is the hands down winner of this honor. Annie's fait accompli was making problems disappear into thin air. One memorable escapade involved a litigious patient falling from an allegedly defective hospital bed. The bed had been sequestered in an unused room awaiting inspection by a representative from the plaintiff's lawyer.  Annie contacted a nursing school on the other side of the city and offered them a free bed for their nursing practice lab. All they had to do was provide transportation which was arranged through a friendly police officer hanging out in the ER. In Chicago, paddy wagons are called "squadrols" and they just happened to perfectly accommodate a hospital bed.

The Marcel Marceau Award goes to one of my favorite OR colleagues, Janess, who was a strict devotee of that old school axiom that scrub nurses are better seen than heard. Every OR nurse recognizes the wrist flick gesture for a needle holder or the index, 2nd finger sign for scissors. but Janess had a few special movements that were just between us. A modified throat slashing gesture meant that our dreaded nemesis, Alice, the noisebarfing supervisor was approaching with her usual dose of venom and it was time to lay low. She also had a unique taffey pulling like gesture for a retractor that was most impressive and cemented her qualifications to receive such an esteemed honor.

The next award is really something special and it's called the starfish award, coined after the aquatic creature's unique ability to heal on its own accord by growing new limbs. Corazon Amuro is the deserving recipient of this honor.

She was the sole survivor of a demented serial killer named Richard Speck who invaded a Chicago apartment where 9 student nurses were living. Ms. Amuro was the sole survivor and witnessed the blood bath from beneath a bed as Speck strangled, stabbed, and slashed his way through the tenement.

When asked about her recovery she replied that there was no counseling and that she sustained herself by working hard as a nurse. To her, nursing was not a means to an end. Nursing was the end itself. She took care of others and was grateful for her 1966 salary of about $4.00 an hour.


Friday, October 29, 2021

O.R. Poem

 Find me a place

where the overheads shine bright

and the hollering gives fright.

Find me a suture that closes just right

and a patient that awakes without

a pathology that gives a great fright.


I remember a young scrub nurse

hiding from the world.

Find me all these things

And that is where you'll find me.